Thymosin alpha-1: the sepsis trials
The earlier study offered hope. The larger one asked the same urgent survival question and came back without a clear benefit.
ETASS / TESTS
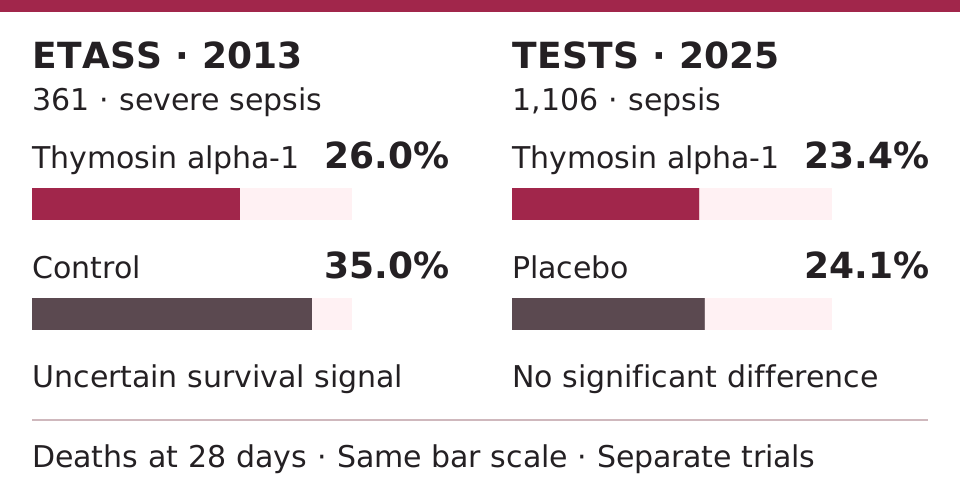
The names are easy to confuse. ETASS was the earlier severe-sepsis trial; TESTS was the later, larger sepsis trial. Reading the earlier paper alone leaves a much more encouraging impression than reading the pair.
In ETASS, involving 361 patients with severe sepsis, 28-day mortality was 26.0% with thymosin alpha-1 and 35.0% in controls. Nonstratified P=0.062 and log-rank P=0.049 put the survival finding in uncertain territory. A measure of monocyte immune function improved too. The early enthusiasm is understandable: a biological change and a possible survival signal were pointing in the same direction.
The phase 3 TESTS trial involved 1,106 adults across 22 centres. It was double blinded and placebo controlled. Mortality at 28 days was 23.4% with thymosin alpha-1 and 24.1% with placebo; hazard ratio 0.99, 95% CI 0.77-1.27, P=0.93. The trial found no statistically significant survival benefit.
Those are separate patient groups, so the percentages cannot establish which trial's patients did better because of treatment. Within TESTS, the comparison against placebo is the decisive one. After TESTS, I'd place far less confidence in a sepsis survival claim.
What does thymosin alpha-1 do?
Thymosin alpha-1 is a naturally occurring peptide; the manufactured version, thymalfasin, has the same sequence. The comprehensive review describes its effects on immune-cell maturation and signalling. Some of those cells help detect an infection, while others develop a more targeted response to it.
The biology is more interesting than the phrase “immune boost” suggests. Alongside actions that support an active response, proposed regulatory actions can restrain excessive inflammation. Sepsis itself involves a dangerous response to infection, so simply turning immunity up would be an inadequate description of the treatment idea.
I'd give a precise account of that biology a fair hearing. The survival result still governs the sepsis claim. A convincing explanation for an intervention can survive even when its hoped-for clinical benefit fails to appear.
COVID-19; oncology
A retrospective study of 76 people with severe COVID-19 associated thymosin alpha-1 treatment with lower mortality and changes in T cells, the immune cells involved in recognising and responding to infection. The researchers also reported fewer signs of T-cell exhaustion, a state in which those cells respond less effectively.
This was a look back at care, with treatment chosen outside a randomised comparison. Other differences between treated and untreated patients could have contributed to the mortality finding. The cell findings help explain the hypothesis; the study design leaves the cause of the survival difference unresolved.
The cancer review examines thymosin alpha-1 alongside other therapies. It considers an adjunct—something added to another treatment—in a mix of preclinical and clinical oncology work. I would be misrepresenting that record if I turned it into a claim that thymosin alpha-1 treats cancer by itself. Each combination and illness needs its own assessment.
International use; US non-approval
The clinical review reports approvals in more than 35 countries and a generally well-tolerated profile, most often with local irritation, redness or discomfort at the injection site. Thymosin alpha-1 has no medicine approval in the United States. International experience gives it a substantial history, while the sepsis findings demonstrate how much an individual indication can still disappoint.
Immune effects also raise theoretical concerns in autoimmune disease and after organ transplantation, when other treatment may deliberately suppress an immune response. These are reasons for clinical assessment, rather than demonstrated transplant or autoimmune harms in the trials discussed here. Pregnancy and breastfeeding safety remain uncertain.
Community accounts describe fewer illnesses, steadier energy, mild reactions or no noticeable change. These are anecdotal accounts, not clinical evidence. Their uncertain causes and unverified products leave them unable to resolve the questions raised by the controlled trials.
For the wider context, the comparison of clinical outcomes sets this survival record beside the fat, weight and recovery findings elsewhere on the site.